


When Research Moves Forward, Who Gets to Move Forward With It?

Research without access for those who need it most remains a theory on paper.

That thought stayed with me throughout the World Conference on Lung Cancer (WCLC26) in Seoul – but particularly during the moments when I had the opportunity to bring the patient perspective into rooms dominated by science, data and clinical research.

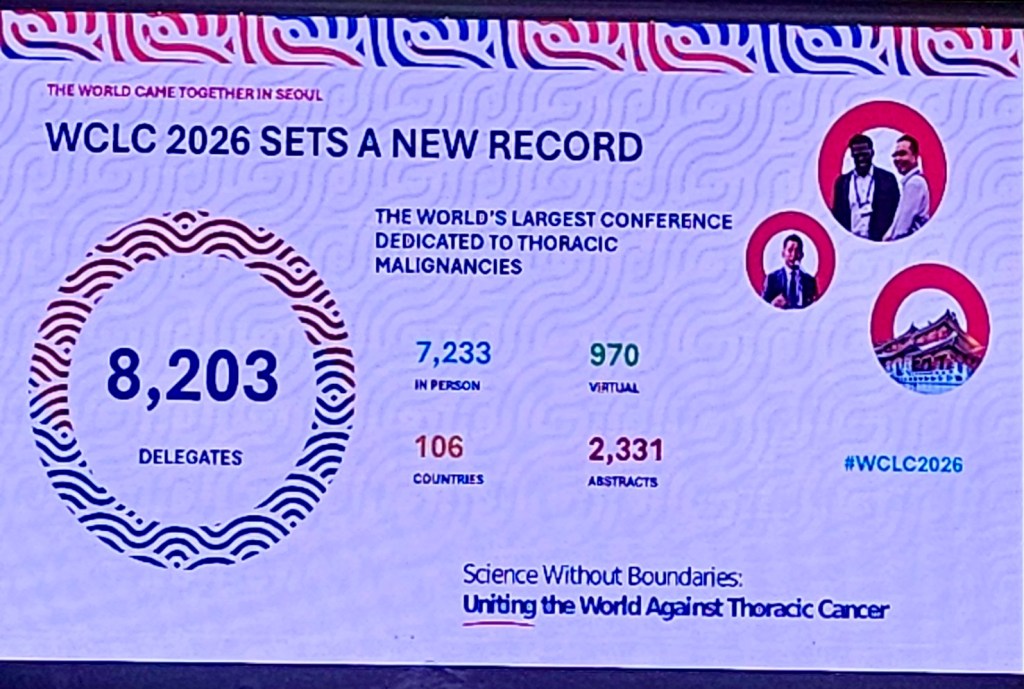
WCLC brought together more than 8,000 delegates from 106 countries, with over 2,000 abstracts – a remarkable global gathering of researchers, clinicians, investigators, scientists, policymakers and patient advocates working toward a better future for people living with lung cancer.

But for me, the most important question was not simply how far lung cancer research has come.

It was:

How do we make sure that progress reaches the patients who need it most?

Bringing access into the clinical conversation

One of the most meaningful opportunities for me at WCLC26 was being invited as a speaker for a CME-accredited session attended by doctors and other healthcare professionals, where I spoke about access, equity and the patient perspective in cancer care and research.

Speaking to a room where healthcare professionals is also present, a different responsibility from speaking to only a patient advocacy audience.

Clinicians and researchers see the world through evidence, treatment outcomes, clinical pathways and scientific possibilities.

Patients experience the same system through very different questions:

Can I access this treatment?

Can I afford it?

Is there a clinical trial I can participate in?

Will someone explain my options to me?

Does the healthcare system where I live give me the same opportunities as someone elsewhere in the world?

Scientific progress answers some questions.

Patients live with the questions that remain.

And that is why patient voices need to be part of the conversation – not after research has been completed, but while we are deciding what research matters, how it is conducted and how its outcomes can reach people.

The evidence behind the conversation

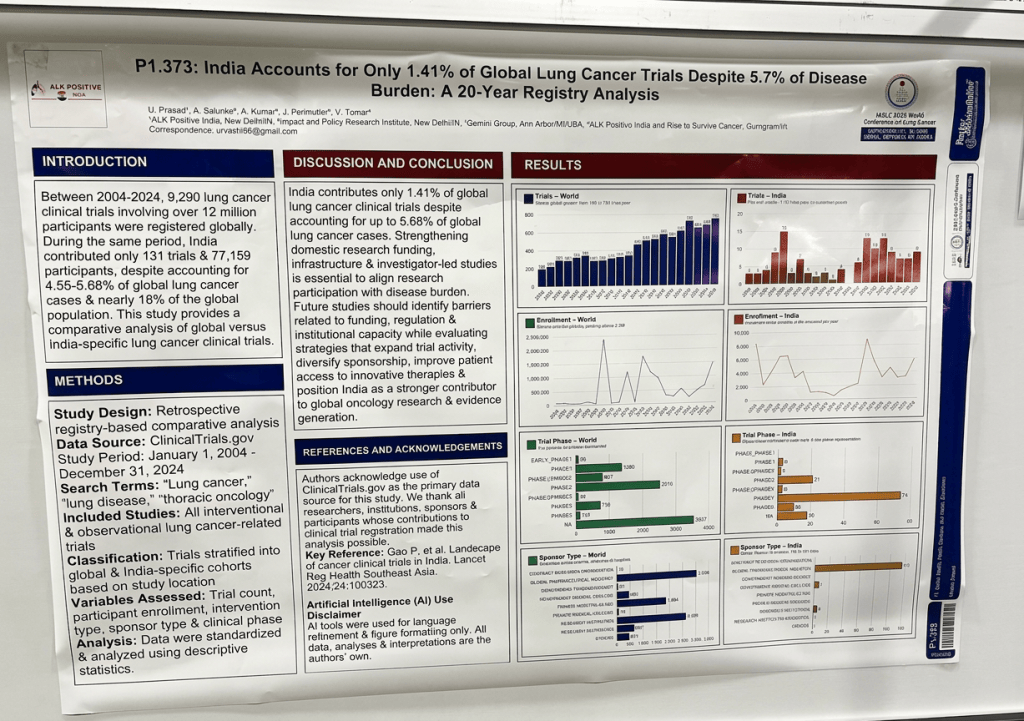
That conversation was particularly meaningful because I was also able to present research examining India’s representation in global lung cancer clinical trials over a 20-year period.

The finding was striking:

India accounts for approximately 5.7% of the global lung cancer disease burden, yet contributed only 1.41% of global lung cancer trials in the registry analysis.

Numbers like these should make us pause.

Clinical trials are not simply mechanisms for developing new medicines. They are also pathways through which patients can gain access to innovation, contribute to scientific knowledge, and ensure that research addresses the realities of different populations.

When countries and populations carrying a significant disease burden are underrepresented in research, we need to ask whether the evidence being generated fully reflects the diversity of patients who will eventually need those treatments.

This is particularly important for lower- and middle-income countries, where the burden of cancer is substantial but access to research and clinical trials can remain uneven.

India cannot simply be a recipient of global cancer innovation.

India – and other underrepresented regions – need to be part of creating the evidence that shapes the future of cancer care.

Humanizing research in the press room

Another special opportunity was participating in the IASLC press briefing alongside leading researchers and investigators.

Scientific research is often presented through numbers – response rates, survival curves, biomarkers, trial populations and statistical outcomes.

All of that is essential.

But behind every number is a person.

During the press briefing, I had the opportunity to bring the patient perspective into discussions around the research being presented – helping humanize the science and reminding us that every clinical endpoint ultimately represents someone’s life, someone’s family and someone’s hope.

This is one of the roles I value most as a patient advocate:

connecting the science with the person behind the science.

Researchers may ask whether an intervention works.

Patients also ask whether they can reach it.

Researchers may measure efficacy.

Patients experience effectiveness through quality of life, side effects, affordability, accessibility and the ability to continue living their lives.

Both perspectives are necessary.

Innovation is not the same as access

The world is moving rapidly in cancer research. New targeted therapies, immunotherapies, diagnostics, biomarkers and increasingly sophisticated approaches to precision medicine are changing what is possible.

But scientific progress alone does not guarantee health progress.

A treatment that exists but cannot be accessed is not the same as a treatment that is available.

A clinical trial that is technically open to a population but practically inaccessible to that population does not create meaningful inclusion.

And research that does not sufficiently include patients from different parts of the world risks leaving important questions unanswered.

We cannot measure the success of cancer innovation only by how quickly we discover something new. We must also ask how equitably that discovery reaches the people who need it.

Patients must have a seat at the table

Patient involvement in cancer research should not be limited to telling personal stories.

Patients can contribute to conversations about what research questions matter, how trials are designed, what outcomes are meaningful, how information is communicated, what barriers prevent participation, and what makes care genuinely patient-centred.

And patient voices from India and other lower- and middle-income countries need to be part of these conversations from the beginning – not added at the end.

Representation matters.

Geography matters.

Affordability matters.

Healthcare infrastructure matters.

And lived experience matters.

If we want truly global cancer research, then global participation cannot simply mean inviting the world to attend a conference. It must mean enabling the world to participate in the research itself – and benefit from what that research produces.

The conversation cannot end in Seoul

WCLC26 gave me the opportunity to contribute in three very different but connected ways: speaking to healthcare professionals about access and equity, presenting research that highlighted an important gap in clinical trial participation, and bringing the patient perspective into conversations around emerging research at the press briefing.

For me, these were not three separate experiences.

They were three parts of the same conversation.

Science tells us what is possible.
Research tells us what works.
Patients remind us who it needs to work for.

The challenge now is to build a clinical research ecosystem where patients in India, Africa, Southeast Asia, Latin America and other underrepresented regions are not merely recipients of innovations developed elsewhere, but active participants in creating the evidence and innovations that will shape their own futures.

How do we make trials more accessible?

How do we address affordability?

How do we strengthen research infrastructure?

How do we improve awareness and referral pathways?

How do we ensure regulatory and healthcare systems can support innovation while protecting patients?

And perhaps most importantly:

How do we ensure that the postcode, passport or bank balance of a patient does not determine whether they have access to tomorrow’s cancer care?

These are not questions that researchers can answer alone.

They require clinicians, investigators, pharmaceutical companies, regulators, policymakers, healthcare systems and — critically — patients and caregivers to work together.

WCLC reminded me that science can move incredibly fast.

Our responsibility is to make sure access keeps pace with it.

Listen. Learn. Advocate. Act.

Because the future of cancer research should not belong only to the patients who can reach it.

It should belong to all of us.

Invited to the Table, But Not Enabled to Be There

Patient advocacy should not mean unpaid, unsupported participation

There is another uncomfortable dimension to this conversation.

In many mature healthcare and research ecosystems globally, patient engagement is increasingly recognised as a professional contribution, not merely voluntary goodwill. Patient advocates participating in conferences, advisory boards, policy consultations, research initiatives and industry discussions may receive appropriate support for travel, accommodation and other participation-related expenses – and, where the nature of the engagement warrants it, honoraria for their time, expertise and contribution.

The principle is simple:

Lived experience has value.

A patient advocate is not simply a person who happens to have had cancer. They may bring years of experience navigating treatment, healthcare systems, clinical research, financial toxicity, quality-of-life issues and the realities faced by patients and caregivers.

That expertise deserves recognition.

In India, however, we still have a long way to go.

Patient voices are too often treated as an add-on, a symbolic presence or a formality rather than as an essential stakeholder voice. Patients may be invited to a panel, given a few minutes to speak or included in a photograph – but meaningful participation, representation and support are still far from being the norm.

And this creates a paradox.

We say we want patient-centric healthcare, but the patient is often the least empowered participant in the room.

We talk about equity, while the person representing lived experience may have to personally absorb the cost of travelling hundreds or thousands of kilometres to participate.

We talk about valuing patient voice, while expecting that voice to be provided entirely on a voluntary basis, even when other stakeholders are participating as professionals representing well-resourced institutions.

We need to ask ourselves honestly:

Are we inviting patients because we genuinely value what they bring – or because patient inclusion has become something we feel we are expected to demonstrate?

There is a difference between patient presence and patient participation.

And there is an even bigger difference between participation and meaningful influence.

India’s patient advocacy ecosystem is evolving rapidly, and there are certainly organisations, researchers, clinicians, policymakers and industry leaders who are doing this well. But these examples need to become the norm rather than the exception.

Patient advocates should not have to repeatedly justify why their travel needs to be supported.

They should not have to prove that their time has value.

And they should not have to choose between contributing to healthcare policy and personally bearing costs that other stakeholders would ordinarily not be expected to bear.

If we genuinely believe that nothing about patients should be decided without patients, then we must also create the practical conditions that allow patients to be present, heard and respected.

Patient inclusion cannot remain a showpiece. It has to become a standard.

7 years, 2 promises, and 3000+ km…..I took her to Ladakh!!

Some journeys take days.

Some take years.

This one took 14 years.

When Kusum and I got married, she shared her love for adventure, the mountains, and her dream of travelling together to Mussoorie, Kashmir, and Ladakh.

We visited Mussoorie on our honeymoon.

Then life changed.

In 2012, at just 29 years of age, Kusum – who had never smoked – was diagnosed with Stage IV lung cancer. By then, the cancer had already spread to her brain, bones, adnexa, and ovaries.

Yet, in 2013, post chemotherapy and whole brain radation, we travelled to Kashmir together to celebrate her birthday.

But one dream remained unfinished.

Ladakh.

Her oncologists advised against travelling there because of the significant high altitude of Himalayas and low oxygen levels.

So that dream quietly stayed with us.

After Kusum passed away, I kept her ashes with me for seven years.

Not because I couldn’t let go…

But because I was waiting for the right time to fulfil a promise – to finally take her to Ladakh.

Becasue, before that, I had another promise to keep.

To raise our son as a single father and help him complete the education that both of us had dreamed of for him.

This year, after watching him graduate from Class 12 with flying colours, I took a motorbike expedition of 3000+ km via multiple majestic himalayan passes, water streams, sand dunes, cold desert, to the world’s highest motorable pass ‘Umling La’ located in ladakh region of Himalayas – carrying white ribbon in my hand to raise lung cancer awareness.

And, yes, I finally took my Kusum to Ladakh 😊

Standing beside the breathtaking waters of Pangong Lake, I said goodbye once again.

Not with tears alone…

But with gratitude.

For the love we shared.

Forever in my heart.

❤️

#RiseToSurviveCancer
#LosingIsNotAnOption
#LoveBeyondLife ❤️
#Ladakh
#LungCancerAwareness

Taking Lung Cancer Awareness to the Top of the World

Yesterday, on World Lung Cancer Day, as I travelled back home – after my motorcycle expedition across the Himalayas to the 𝐰𝐨𝐫𝐥𝐝’𝐬 𝐡𝐢𝐠𝐡𝐞𝐬𝐭 𝐦𝐨𝐭𝐨𝐫𝐚𝐛𝐥𝐞 𝐫𝐨𝐚𝐝, I carried the White Ribbon, to raise Lung Cancer Awareness.

The journey took me through
~ Crossing 8 high mountain passes (3 of the World’s Top 10 Highest Motorable Passes),
~ 6 majestic Himalayan Lakes (including the Highest brackish water high-altitude lakes on earth),
~ High Altitiude Mountain Sickness – Struggle for Oxygen, Breathing – Headache, Vomitting
~ Crossed countless Water Streams and Rivers,
~ Sand Dunes,
~ the Cold Desert,
~ and ever-changing mountain Weather – from Rain and Hailstorms to Scorching Sunshine, Strong Winds, Snow

But this journey wasn’t about reaching a destination with Guinness World Record

It was about carrying a message.

Behind these photographs were 𝐭𝐡𝐨𝐮𝐬𝐚𝐧𝐝𝐬 𝐨𝐟 𝐤𝐢𝐥𝐨𝐦𝐞𝐭𝐫𝐞𝐬 of riding, resilience, and purpose.

For me, this mission is deeply personal.

Having lost my beloved wife, Kusum Malik Tomar, to Stage IV lung cancer, I know firsthand how devastating this disease can be.

In memory of my Kusum, I have dedicate myself to lung cancer awareness and patient advocacy, so that fewer families have to endure what ours did.

Every conversation about lung cancer matters.

Every opportunity to encourage earlier diagnosis matters.

Every effort to improve access to treatment, research, and patient support matters.

𝐁𝐞𝐜𝐚𝐮𝐬𝐞 𝐚𝐰𝐚𝐫𝐞𝐧𝐞𝐬𝐬 𝐡𝐚𝐬 𝐧𝐨 𝐚𝐥𝐭𝐢𝐭𝐮𝐝𝐞 𝐥𝐢𝐦𝐢𝐭.

𝐀𝐧𝐝 𝐛𝐞𝐜𝐚𝐮𝐬𝐞 𝐞𝐯𝐞𝐫𝐲 𝐛𝐫𝐞𝐚𝐭𝐡 𝐦𝐚𝐭𝐭𝐞𝐫𝐬. 🎗️

#lungcancerawareness #losingisnotanoption🚫 #risetosurvivecancer #rideforacause❤️ #airpollution #patientadvocacy #everybreathmatters🫁 #ResearchSavesLives

International Clinical Trials Day

On International Clinical Trials Day, I was invited as a Guest Speaker at number of places including ‘Medanta – The Medicity’, one of India’s leading hospitals, to address medical students, healthcare professionals, industry stakeholders and media.

Standing at the podium, in my volunteer work capacity of patient research advocate, I shared something close to my heart: the urgent need to strengthen patient voices in healthcare decisions and clinical research in India:

• The current realities and perceptions around clinical trials in India

• Why research and innovation matter to patients and families

• Barriers that prevent participation and trust

• What institutions, industry and healthcare leaders can prioritise to improve outcomes

• Why patient advocacy must become part of the healthcare ecosystem

• Why in India, industry & PI struggle for patient recrutiment and at same time why patients struggle to find clinical trials – how to fill this strange but huge gap!!

Every breakthrough treatment exists because research happened.
Every research question should remember the patient behind it.

Research saves lives. Patient voices save time, suffering and missed opportunities.

Thank you to everyone working towards more compassionate, inclusive and patient-centred healthcare.

And a special thank you for all the kind words, encouragement and conversations after the session – it truly meant a lot.

Patient Advocacy at Fortis Cancer Summit 2026

At India’s one of largest medical conference, At Fortis Cancer Summit 2026 in Delhi, spoke about two realities we can no longer ignore:

1) Access

> For most cancer patients in India, the challenge is not just the disease – but access to treatment.
> Even when “gold standard” therapies exist, they are often financially out of reach.
> Ayushman Bharat insurance scheme still hardly covers any targeted therapies – leaving a critical gap.
> Timely access to Research, Clinical Trials, & latest Treatment is still a dream in most cases in India.

We cannot build a system where survival depends on affordability.

2) Awareness

At the conference, our new initiative of lung cancer awareness effort as part of the White Ribbon Project India – We shared the White Ribbon with oncologists, industry leaders, hospitals, non-profits and policymakers – bringing attention to a cause that needs far greater visibility.

Because awareness grows when voices come together. Change will require both – better access to treatment, and stronger collective awareness.

And it was a warm moment to get hand written note from a cancer survivor 🎗️ 💙

#EveryLivesMatters #ResearchSavesLives #LungCancer #PatientAdvocacy #HealthcareAccess #CancerCareIndia #AffordableHealthcare

Single Fathers Are Not a Myth, So Why Are We Invisible?

Seven years ago, my world – and the world of my then 10-year-old son, Suryansh – was irrevocably changed. When my wife, Kusum aka Vibha, passed away after a brave battle with cancer, we were left in a silence that no house is ever prepared for.

In a society that rightly celebrates the strength of single mothers, there is a quiet, overlooked shadow: The Single Father. We are not a myth. Yes, we are very few, especially in India – where you may know thousands of single mothers, but single fathers are rare. But we are here, raising the next generation in the trenches of grief and growth. Yet, for all the space we occupy in our children’s lives, we remain largely invisible to the world.

A Tribute to an Extraordinary Son

If Suryansh ever reads this, I want him to know one thing above all: You are truly an extraordinary boy. The circumstances we faced made you mature well before your age. Throughout this journey, you have been understanding, supportive, caring, and deeply loving. You weren’t just a child being raised; you were a partner in our survival.

But I also want you to know that it was okay to still be a kid. Even the strongest teenagers have a world of things struggling inside them – hormones, the pressure of growing up, and the simple, human need for a mother’s presence. When we fought or cried together, it wasn’t because you weren’t “doing enough” – it was because we were both learning to navigate a void that was never meant to be there. You did great, Suryansh. You always have.

The Village and the Specific Void

We were not alone. My mother – Suryansh’s grandmother – moved in with us to take care of him with immense love. She did everything humanly possible to anchor our home. However, as Suryansh grew, he realized the distinction: a grandmother is a treasure, but she is not a mother. He sought a mother’s unique parenting, and for that, he only had me.

I chose not to remarry – a decision I made happily and with a full heart – because I wanted to ensure my undivided attention and care were focused entirely on our bond. It wasn’t a sacrifice; it was my priority, and it has been the most fulfilling path I could have chosen. I gave myself completely to being the best father I could be, even trying my level best to “be a mother” too.

But the truth is, I didn’t have that “God-given” gift of motherhood. No matter how much I tried, I could never replicate the “golden touch” that mothers naturally possess. Mothers are the most beautiful, amazing beings – no one can truly come near that frequency of care.

The Academic Anchor: Class 5 to Class 12

In our Indian culture, the mother is often the silent engine behind a child’s education. From Class 5 to Class 12- the most defining years of a student’s life- it is usually the mother who manages the schedules, the exams, and the daily discipline of study.

Losing Kusum meant losing that academic foundation. I had to step into a role that was entirely foreign to me, trying to provide the stability and focus that only a mother truly knows how to give. Suryansh and I tried our best together to navigate his studies and excel in academics while through this grief & void, was nothing short of heroic.

The Search for a Map in the Dark

During these last seven years, I was a man trying my best to help a young kid grow in the best possible way, but I was often doing it in total isolation. When I looked for support online or in-person groups in India, I found plenty of resources for single mothers – and they absolutely deserve that support.

But for single fathers? Nothing. It is as if society believes men don’t need emotional communities, or that we don’t feel the same “Am I doing this right?” anxiety. Because we don’t naturally possess that maternal “golden touch,” we actually need more support, more resources, and a community that acknowledges our existence.

Lighting a Candle

I am writing this blog to raise a voice for the men standing in my shoes. I hope this “lights a candle” so that we can stop treating single fathers as an invisible demographic.

To the fathers doing the work: Your commitment is seen, even if the world isn’t looking.

To the sons like Suryansh: Your strength is heroic.

To all those loved ones who jumped in to support a single parent and/ or the kids who lost a parent – just as Suryansh’s grandmother, Smt. Pushpa ji, did for us – Thank you! Your love is the bridge that helped us cross the impossible

The Price of a Seat at the Table

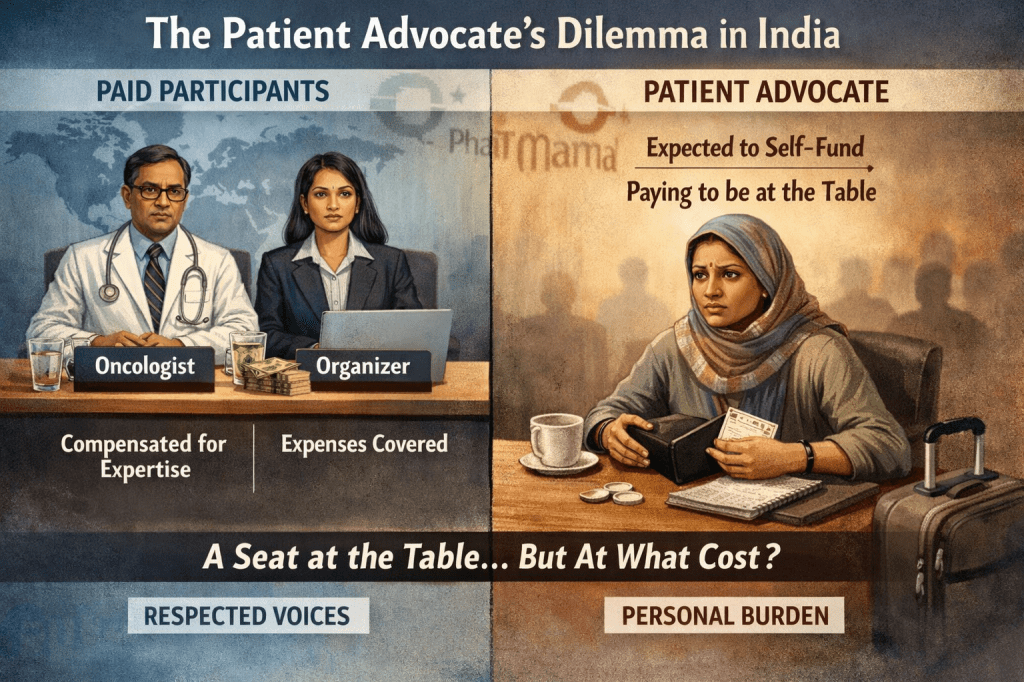
In the global oncology landscape, “Patient Centricity” is everywhere. It’s on corporate banners and in mission statements. But as a patient advocate in India, I often find myself asking: Who is paying for the dignity of that seat at the table?

In the West, it is increasingly standard for pharmaceutical companies and non-profits to offer honoraria to patient advocates. They recognize that lived experience is a specialized, unique expertise that cannot be found in a textbook.

The Reality in India: Inclusion or Illustration?

In India, the story is very different. With rare exceptions, most organizations – including global pharma branches and well-funded non-profits – often treat patient advocates as ornamental rather than essential.

While everyone else in the room is there in a professional capacity, advocates are frequently expected to provide their time and insights for free. Even more concerning is when sponsored events fail to cover basic logistics or travel. In these scenarios:

  • The Oncologist is compensated for their clinical expertise.
  • The Organizer is compensated for their coordination.
  • The Patient Advocate is often expected to self-fund their participation, essentially paying out of their own pocket to represent a community that is already struggling.

The Advocate’s Dilemma

This creates a painful choice:

  • Keep attending: We maintain our hard-won seat at the table, but we risk validating a system that treats our lived experience as a “nice-to-have” add-on rather than a core contribution.
  • Stop attending: We lose our influence, and the conversation reverts to an era where decisions are made about us, without us.

From “Showpiece” to Partnership

We will always be volunteers for our cause – that is where our heart is. But there is a line between volunteering for patients and being used as a showpiece for a corporate agenda. We shouldn’t have to choose between our dignity and our impact. True partnership means that if an advocate’s voice is essential enough to be on the agenda, it is essential enough to be respected with the same equity shown to every other expert in that room.

Beyond the Page: Bringing our Mission to Life on Instagram too

The Power of Connection For years, this blogsite has been a sanctuary for my community – a place where we dive deep into lung cancer research, patient advocacy, and the global policy changes we need in LMICs and beyond. It has been a privilege to connect with readers from 50+ countries.

But as now I work on the memoir for Kusum and push through my own 50-day journey of resilience, and that volunteer work of patient advocacy isn’t just about the words we write; it’s about the lives we lead every day.

Why Instagram? Why Now? I have decided to launch a dedicated public Instagram profile: @risetosurvivecancer.

While this blog will remain the home for my long-form research updates and detailed advocacy reports, Instagram will be the “Live Newsroom” of our mission. It’s where I will share:

  • Daily Resilience: Real-time updates from my 50-day fitness and advocacy challenge.
  • Behind-the-Scenes: Insights into the research lab, global conferences, and the making of the memoir.
  • Travel & Hope: Clips from my journeys (like the recent trip to South Africa) that show the human side of this fight.
  • The Memoir Journey: Exclusive snippets and reflections from the book I am writing for Kusum.

Keeping the Focus I want to be clear: the technical depth and global advocacy work you value on this blog aren’t going anywhere. Instead, Instagram allows a space for us to interact more closely, share quick wins, and build a more visible movement.

Join the Conversation If you have been part of this global community, I invite you to join me on this new platform too. Let’s make our collective voice even louder.

Link to connect at Instagram: https://www.instagram.com/risetosurvivecancer/

Vivek

Why Speaking Up for India and LMICs in Global Healthcare is Non-Negotiable

I recently had the privilege of representing India at a global advisory board meeting for lung cancer. These meetings are vital for shaping the future of oncology, yet a familiar pattern emerged: the discussion on “access” was almost entirely dominated by the landscapes of the US and the European Union.

While the challenges in those regions are real, “access” takes on a completely different meaning in India and other developing nations. In our context, it isn’t just about administrative hurdles; it’s about the fundamental availability of life-saving innovation for millions who are often left out of the global conversation.

The Power of the “Living Experience”

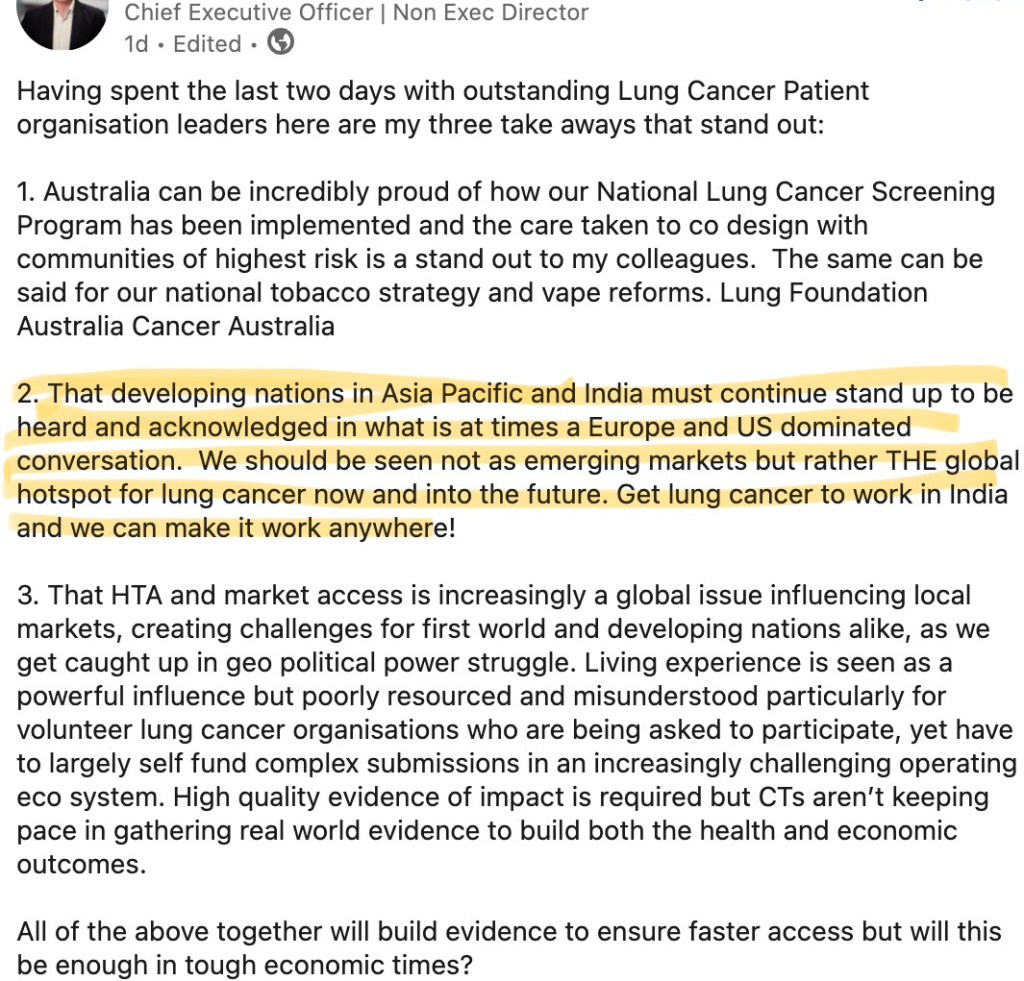
During the sessions, I made it a point to politely but firmly steer the conversation toward the missing voices of India and LMICs. It is easy for global boards to view these regions as “emerging markets,” but the reality is that we are the global hotspots for lung cancer. If we can solve the access puzzle in India, we can solve it anywhere.

I was heartened to see this message resonate. Shortly after the meeting, a senior colleague and representative from Australia shared his takeaways on LinkedIn, specifically highlighting that developing nations in Asia Pacific and India must continue to stand up to be heard.

Why Your Voice Matters

This experience reminded me of three critical truths for advocates:

  • Visibility is the first step to Access: If we aren’t at the table – or if we stay silent while at the table – the world will continue to design solutions that don’t fit our reality.
  • Data + Experience = Impact: Combining Health Technology Assessment (HTA) with the “living experience” of patients creates a narrative that even the most complex geopolitical or economic systems cannot overlook.
  • The Ripple Effect: When you speak up, you aren’t just influencing the person across from you. You are providing the language and the courage for other leaders to carry that message back to their own countries.

Moving Forward

Advocacy is often a long, uphill climb, but seeing the immediate impact of a single intervention at a global meeting is a powerful motivator. We must continue to demand that the global oncology conversation reflects the global reality.

Our voices are not just “participation” – they are the essential evidence required to build a more equitable healthcare future.

No One Should Fight Alone!

Vivek