


Research without access for those who need it most remains a theory on paper.
That thought stayed with me throughout the World Conference on Lung Cancer (WCLC26) in Seoul – but particularly during the moments when I had the opportunity to bring the patient perspective into rooms dominated by science, data and clinical research.
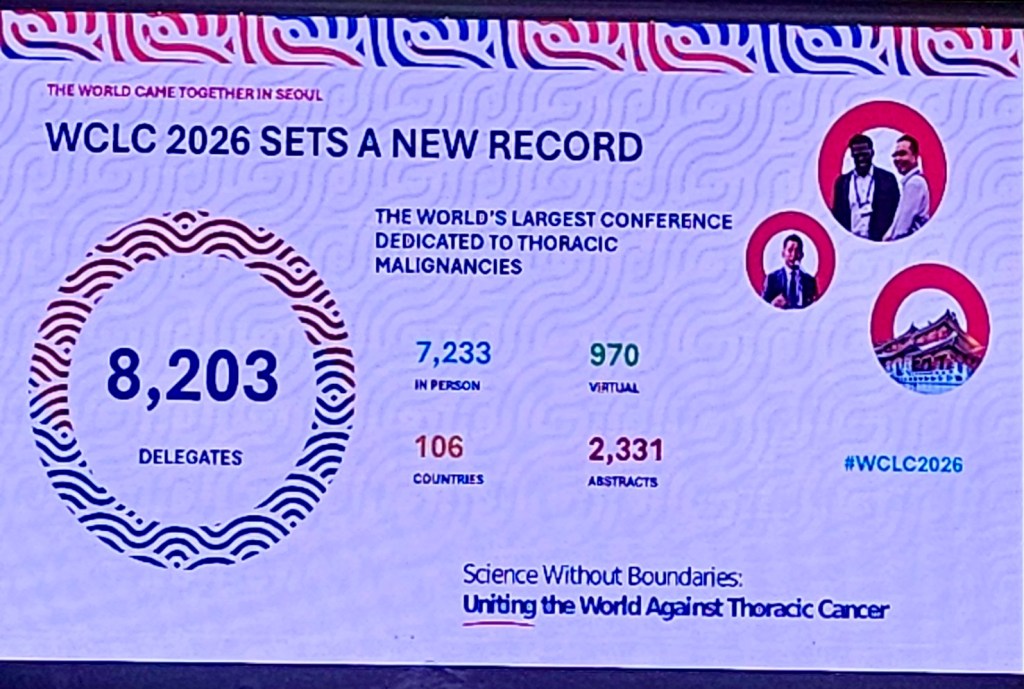
WCLC brought together more than 8,000 delegates from 106 countries, with over 2,000 abstracts – a remarkable global gathering of researchers, clinicians, investigators, scientists, policymakers and patient advocates working toward a better future for people living with lung cancer.
But for me, the most important question was not simply how far lung cancer research has come.
It was:
How do we make sure that progress reaches the patients who need it most?
Bringing access into the clinical conversation
One of the most meaningful opportunities for me at WCLC26 was being invited as a speaker for a CME-accredited session attended by doctors and other healthcare professionals, where I spoke about access, equity and the patient perspective in cancer care and research.
Speaking to a room where healthcare professionals is also present, a different responsibility from speaking to only a patient advocacy audience.
Clinicians and researchers see the world through evidence, treatment outcomes, clinical pathways and scientific possibilities.
Patients experience the same system through very different questions:
Can I access this treatment?
Can I afford it?
Is there a clinical trial I can participate in?
Will someone explain my options to me?
Does the healthcare system where I live give me the same opportunities as someone elsewhere in the world?
Scientific progress answers some questions.
Patients live with the questions that remain.
And that is why patient voices need to be part of the conversation – not after research has been completed, but while we are deciding what research matters, how it is conducted and how its outcomes can reach people.
The evidence behind the conversation
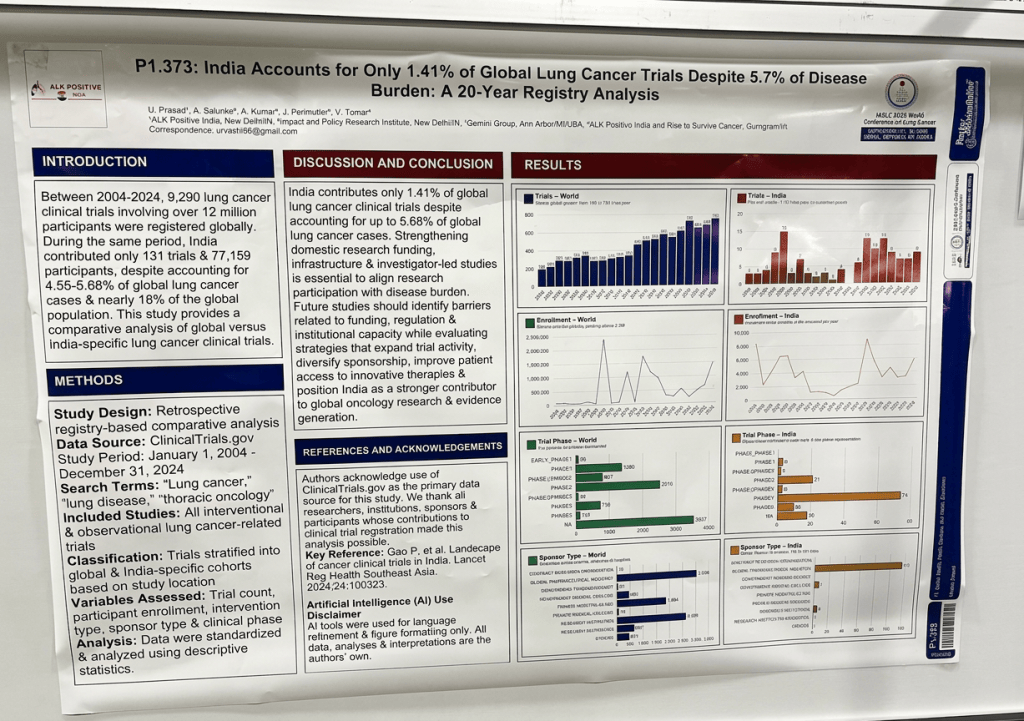
That conversation was particularly meaningful because I was also able to present research examining India’s representation in global lung cancer clinical trials over a 20-year period.
The finding was striking:
India accounts for approximately 5.7% of the global lung cancer disease burden, yet contributed only 1.41% of global lung cancer trials in the registry analysis.
Numbers like these should make us pause.
Clinical trials are not simply mechanisms for developing new medicines. They are also pathways through which patients can gain access to innovation, contribute to scientific knowledge, and ensure that research addresses the realities of different populations.
When countries and populations carrying a significant disease burden are underrepresented in research, we need to ask whether the evidence being generated fully reflects the diversity of patients who will eventually need those treatments.
This is particularly important for lower- and middle-income countries, where the burden of cancer is substantial but access to research and clinical trials can remain uneven.
India cannot simply be a recipient of global cancer innovation.
India – and other underrepresented regions – need to be part of creating the evidence that shapes the future of cancer care.
Humanizing research in the press room
Another special opportunity was participating in the IASLC press briefing alongside leading researchers and investigators.
Scientific research is often presented through numbers – response rates, survival curves, biomarkers, trial populations and statistical outcomes.
All of that is essential.
But behind every number is a person.
During the press briefing, I had the opportunity to bring the patient perspective into discussions around the research being presented – helping humanize the science and reminding us that every clinical endpoint ultimately represents someone’s life, someone’s family and someone’s hope.
This is one of the roles I value most as a patient advocate:
connecting the science with the person behind the science.
Researchers may ask whether an intervention works.
Patients also ask whether they can reach it.
Researchers may measure efficacy.
Patients experience effectiveness through quality of life, side effects, affordability, accessibility and the ability to continue living their lives.
Both perspectives are necessary.
Innovation is not the same as access
The world is moving rapidly in cancer research. New targeted therapies, immunotherapies, diagnostics, biomarkers and increasingly sophisticated approaches to precision medicine are changing what is possible.
But scientific progress alone does not guarantee health progress.
A treatment that exists but cannot be accessed is not the same as a treatment that is available.
A clinical trial that is technically open to a population but practically inaccessible to that population does not create meaningful inclusion.
And research that does not sufficiently include patients from different parts of the world risks leaving important questions unanswered.
We cannot measure the success of cancer innovation only by how quickly we discover something new. We must also ask how equitably that discovery reaches the people who need it.
Patients must have a seat at the table
Patient involvement in cancer research should not be limited to telling personal stories.
Patients can contribute to conversations about what research questions matter, how trials are designed, what outcomes are meaningful, how information is communicated, what barriers prevent participation, and what makes care genuinely patient-centred.
And patient voices from India and other lower- and middle-income countries need to be part of these conversations from the beginning – not added at the end.
Representation matters.
Geography matters.
Affordability matters.
Healthcare infrastructure matters.
And lived experience matters.
If we want truly global cancer research, then global participation cannot simply mean inviting the world to attend a conference. It must mean enabling the world to participate in the research itself – and benefit from what that research produces.
The conversation cannot end in Seoul
WCLC26 gave me the opportunity to contribute in three very different but connected ways: speaking to healthcare professionals about access and equity, presenting research that highlighted an important gap in clinical trial participation, and bringing the patient perspective into conversations around emerging research at the press briefing.
For me, these were not three separate experiences.
They were three parts of the same conversation.
Science tells us what is possible.
Research tells us what works.
Patients remind us who it needs to work for.
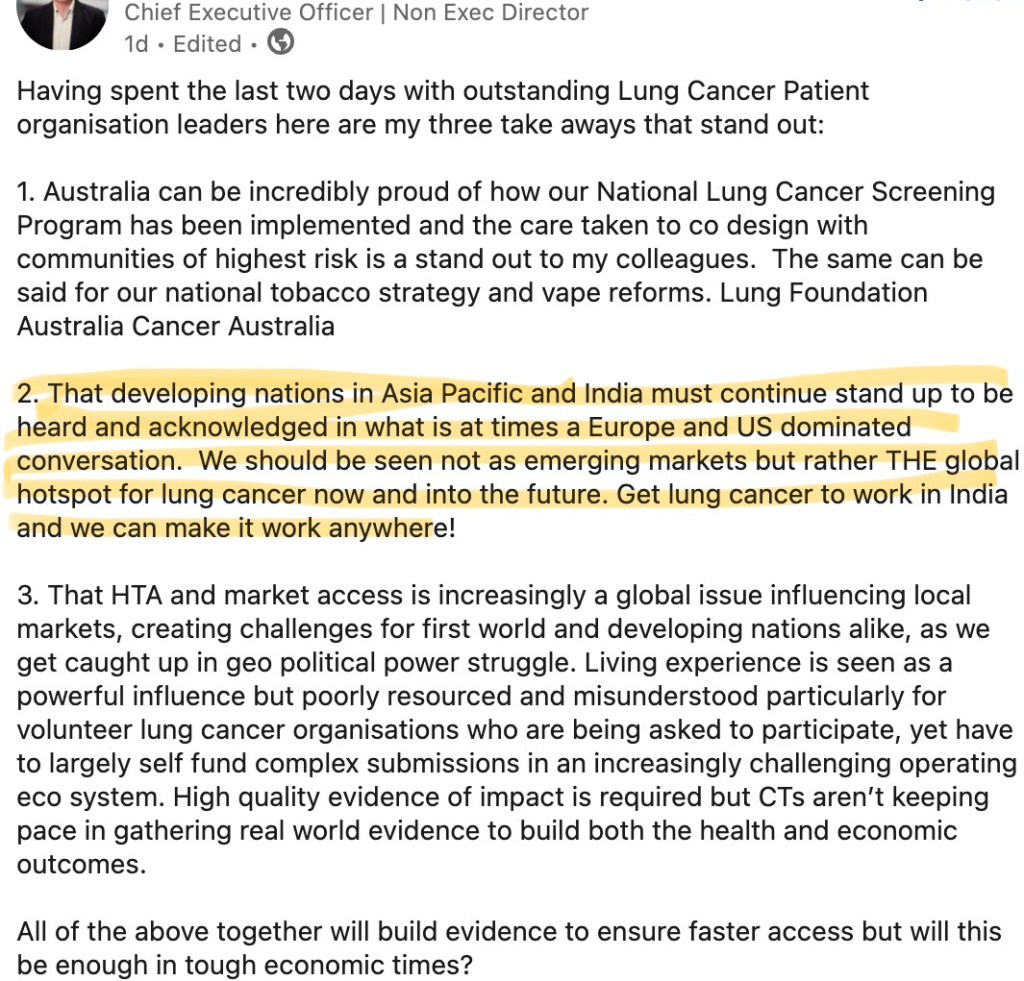
The challenge now is to build a clinical research ecosystem where patients in India, Africa, Southeast Asia, Latin America and other underrepresented regions are not merely recipients of innovations developed elsewhere, but active participants in creating the evidence and innovations that will shape their own futures.
How do we make trials more accessible?
How do we address affordability?
How do we strengthen research infrastructure?
How do we improve awareness and referral pathways?
How do we ensure regulatory and healthcare systems can support innovation while protecting patients?
And perhaps most importantly:
How do we ensure that the postcode, passport or bank balance of a patient does not determine whether they have access to tomorrow’s cancer care?
These are not questions that researchers can answer alone.
They require clinicians, investigators, pharmaceutical companies, regulators, policymakers, healthcare systems and — critically — patients and caregivers to work together.
WCLC reminded me that science can move incredibly fast.
Our responsibility is to make sure access keeps pace with it.
Listen. Learn. Advocate. Act.
Because the future of cancer research should not belong only to the patients who can reach it.
It should belong to all of us.



















 Rise To Survive Cancer
